
Pain education and graded exercise therapy, alongside treatment of the cause
Our exercise physiologist, Jessica Coombe (AEP), has both clinical and personal experience of nerve injury — she rehabilitated her own and studied the area closely in doing so.
We commonly see patients with burning, tingling, numbness or pins-and-needles — often in the feet or hands, frequently worse at night — who have been advised to manage it with medication alone.
Many have diabetic peripheral neuropathy and want to take an active role rather than watch and wait. Others have nerve pain running down the leg from a disc bulge or sciatica — often driven by how they move and load the spine — with a back or leg that has become sensitive to activity.
A common thread is pain that medication has only partly controlled, and a body that has become harder to move and load. Highly complex pain conditions, such as complex regional pain syndrome (CRPS), are outside the scope of this service — if a pain specialist is the better path, we will tell you at the discovery call.
Nerve pain is usually managed with medication alone — commonly pregabalin (Lyrica), duloxetine (Cymbalta) or amitriptyline. These have a role, but they address the symptom and leave the movement, strength and cause untouched. Treatment here adds the parts medication does not reach.
Exercise for nerve and muscle function. In diabetic peripheral neuropathy, aerobic training improves nerve conduction and neuropathic symptoms, and combined aerobic and resistance training reduces symptoms and improves muscle function — safely, even with reduced sensation. It also rebuilds the strength and balance neuropathy erodes, which is what reduces the risk of falls.
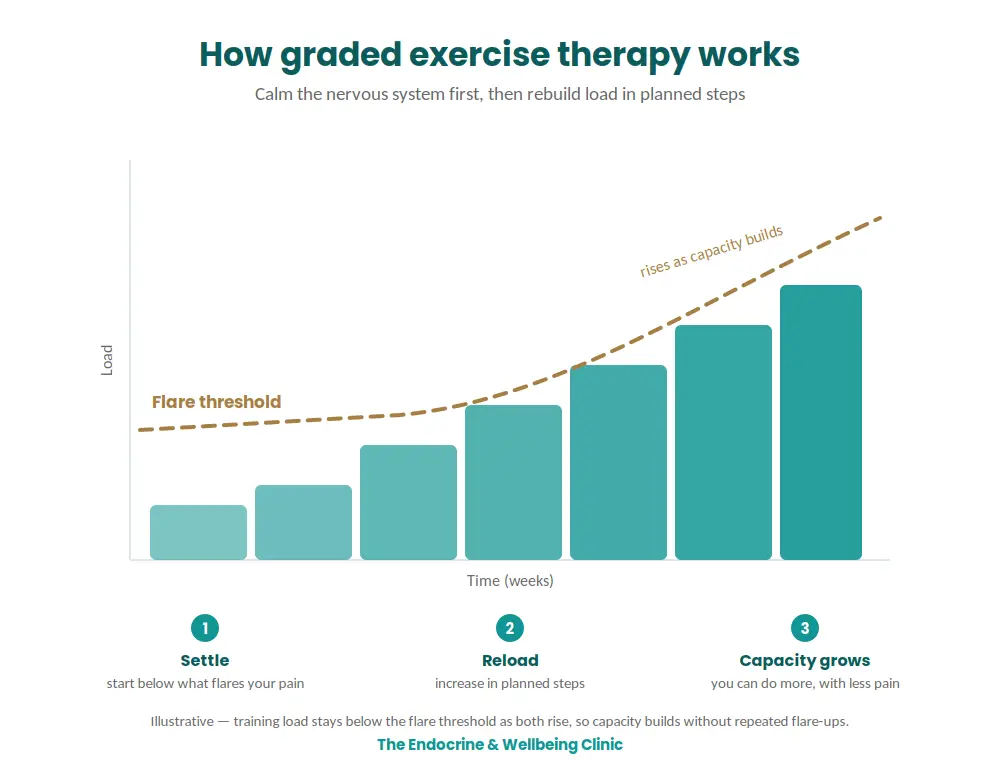
Pain education and graded exercise therapy Persistent nerve pain is rarely just a signal from the affected tissue — over time the nervous system itself becomes protective and turns the volume up, so movements that are safe begin to hurt. Treatment starts by explaining what is actually driving your pain, because understanding it changes how the nervous system responds to it. From there the approach is graded exercise therapy: begin at a level your nervous system tolerates, let it settle, then increase the load in planned steps. The aim is to calm an over-protective nervous system first, then progressively rebuild the loading capacity of the affected area — so you finish able to do more, not just hurting less.
Treating the underlying cause. Where diabetes is driving the neuropathy, its progression slows when blood glucose is controlled. Dr Isobelle Smith manages the metabolic driver directly, and exercise itself improves glycaemic control — so the program addresses cause and symptom together.
Balance and falls prevention. Reduced sensation in the feet changes standing and walking, and the main downstream risks are falls and foot injury. Balance and gait are assessed and trained specifically, and foot-care needs flagged early.

It is a reasonable worry — nerve pain often flares with activity, and many people have learned to protect the area by doing less. The problem is that doing less steadily shrinks what the body can tolerate, so the same tasks provoke more pain over time. Graded exercise therapy works in the opposite direction: it starts below your flare threshold, gives the nervous system time to settle, and increases load in steps small enough that your capacity grows without repeated flare-ups. Short-lived soreness after exercise can occur and is not a sign of new damage. Where diabetes is driving the neuropathy, the exercise does double duty — it also improves the blood glucose control that protects the nerves themselves.
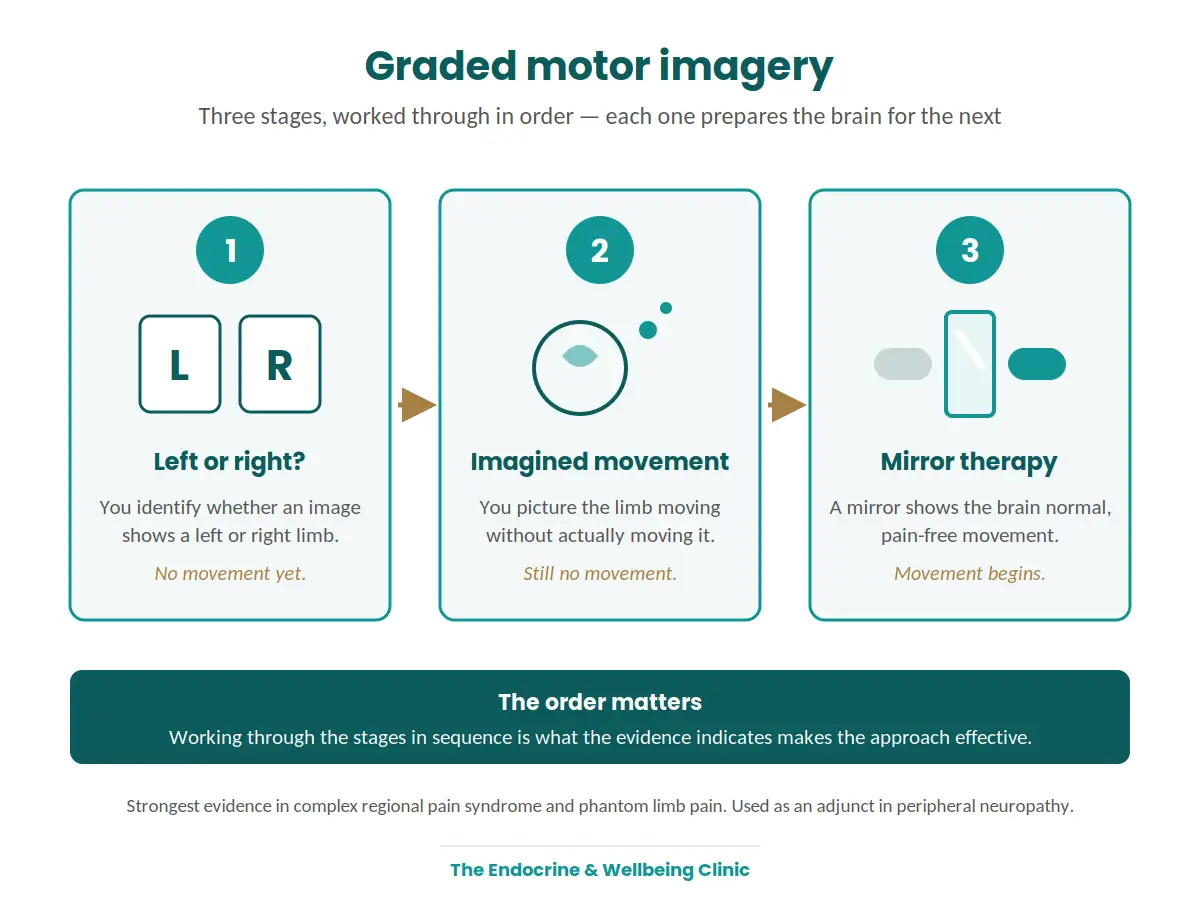
No. Mirror therapy and graded motor imagery do not reverse structural nerve loss. Their strongest evidence is in CRPS, phantom limb pain and post-stroke movement; in diabetic and other peripheral neuropathies they are an adjunct. What they can do is reduce pain and improve how a painful or clumsy limb moves.
In diabetic peripheral neuropathy, aerobic training improves nerve conduction and neuropathic symptoms, and combined aerobic and resistance training reduces symptoms and improves muscle function. Exercise also improves blood glucose control, which is the underlying driver.
Yes, when it is prescribed and supervised. People with reduced sensation can safely do aerobic and resistance training. We match the exercise to your sensation and check your feet, so you get the benefit without the risk.
No. It works alongside it. Pain medication and exercise do different jobs — we add the movement, strength and cause-management that medication does not reach. Any change to medication is a decision for your GP or specialist.
No referral is required to book. If you have a chronic condition such as diabetes, your GP may be able to refer you under a chronic disease management plan for a Medicare rebate — ask us and we can explain how it works.
The Endocrine & Wellbeing Clinic
Phone: (02) 9870 3256
Locations: Balmain (inner west Sydney) and Telehealth Australia-wide
Affiliated with: ESSA (Exercise and Sports Science Australia), ANZBMS, Endocrine Society of Australia
This page is not a substitute for individual medical advice. Book a consult for assessment specific to your situation.